

AirCurve 11 Integration Guide for Bilevel Sleep Therapy Workflows
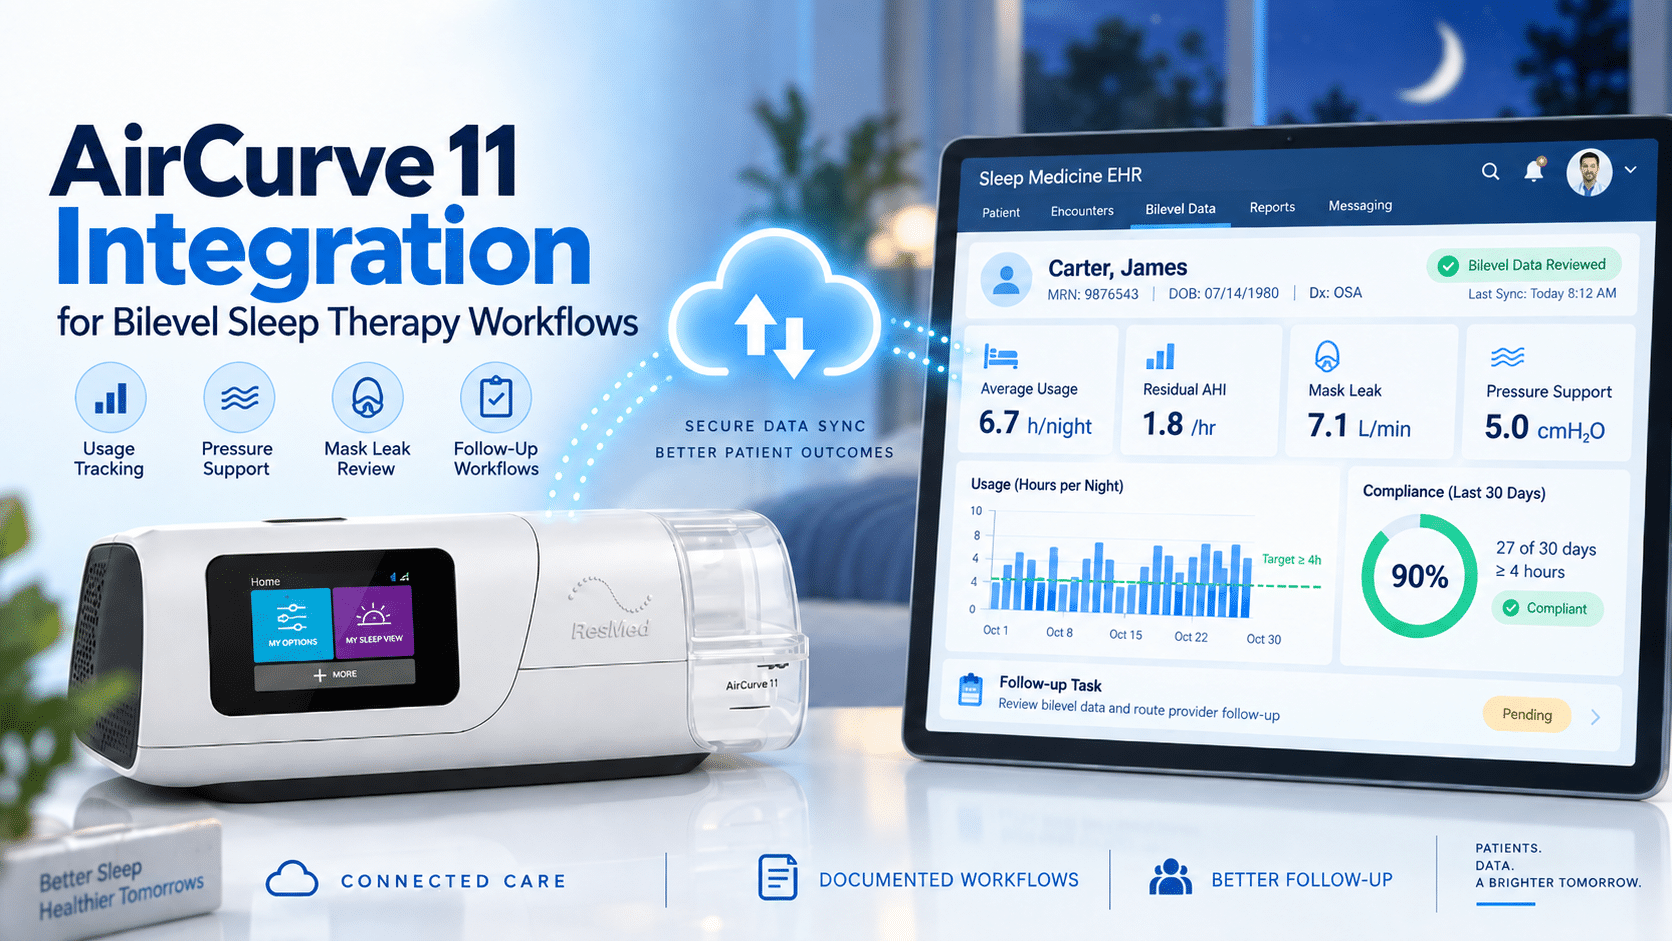
AirCurve 11 Integration for Bilevel Sleep Therapy Workflows
Bilevel therapy patients often require more detailed follow-up than standard CPAP-only patients. They may have higher pressure needs, pressure intolerance, persistent residual events, mask leak challenges, comorbid respiratory concerns, or a history of struggling with PAP adherence. For sleep physicians, sleep lab managers, RPSGTs, DME/HME operators, and practice administrators, this makes AirCurve 11 integration an important workflow topic.
ResMed describes AirCurve 11 bilevel devices as machines for therapy users who benefit from greater pressure support, using two pressure level settings: a higher pressure during inhalation and a lower pressure during exhalation. ResMed also states that AirCurve 11 includes myAir, Care Check-In, and Personal Therapy Assistant to help patients start therapy and stay on track.
For a sleep medicine practice, the goal is not simply to know that a patient is using an AirCurve 11 device. The real goal is to make bilevel follow-up organized, documented, and actionable inside a Sleep Medicine EHR.
That means the care team should be able to review bilevel adherence, usage hours, pressure support, mask leak, residual AHI or residual events, patient-reported barriers, and compliance documentation through the appropriate ResMed workflow, such as AirView. Then those findings should be documented in the EHR, routed to the right staff member, connected to patient portal communication, and available for follow-up and revenue cycle needs.
A strong AirCurve 11 integration strategy should support clinical oversight without claiming that every EHR receives real-time device data or guaranteed direct API access. Unless vendor documentation confirms a specific interface, practices should describe the workflow as AirView review plus EHR documentation, report management, task routing, patient communication, and compliance follow-up.
Why AirCurve 11 Workflows Are Different From Standard CPAP Follow-Up
AirCurve 11 patients are often not simple CPAP setup patients. Bilevel PAP therapy may be used when patients benefit from different inspiratory and expiratory pressure levels. ResMed explains that bilevel devices use a higher pressure when the patient inhales and a lower pressure to make exhalation easier.
That difference matters operationally. A standard CPAP follow-up may focus heavily on usage hours, mask leak, and basic compliance. Bilevel follow-up may require more careful review of pressure support, IPAP/EPAP settings, residual events, leak, comfort complaints, and provider interpretation.
For example, a bilevel patient may report that therapy feels too forceful, that exhalation is uncomfortable, that the mask leaks at higher pressures, or that they are still waking up tired despite using the device. In that case, the EHR workflow should not simply mark the patient as “compliant” or “non-compliant.” It should help the team document what was reviewed, what the patient reported, who needs to respond, and whether provider review is required.
AirCurve 11 Integration: What It Should Mean in a Sleep Medicine EHR
AirCurve 11 integration should be understood as a connected workflow between bilevel device data review and sleep medicine follow-up documentation.
A practical workflow may include:
- Reviewing AirCurve 11 therapy data through AirView or another approved ResMed-supported workflow.
- Documenting bilevel adherence, usage hours, leak, pressure support, residual AHI, and patient concerns in the Sleep Medicine EHR.
Attaching, referencing, or summarizing compliance and therapy reports. - Routing follow-up tasks to the provider, RPSGT, sleep technologist, DME/HME coordinator, care coordinator, or billing team.
Sending patient portal messages for education, reminders, or follow-up questionnaires. - Tracking whether outreach was completed and whether provider interpretation is needed.
- ResMed describes AirView as a secure, cloud-based system that helps healthcare professionals manage patients with sleep-disordered breathing and respiratory insufficiency, access patient data, share clinical insights, and reduce costs related to follow-up.
- ResMed also notes that AirCurve 11 VAuto supports AirView, allowing providers to view insights and reports, manage patient records, and troubleshoot remotely.
The Sleep Medicine EHR should complement this process. It should not replace AirView, physician interpretation, or clinical judgment. Instead, the EHR should make sure the practice has a clear record of what happened after the data was reviewed.
What AirCurve 11 Data Matters Most?
A bilevel follow-up workflow should look beyond basic CPAP compliance. The most useful data points include usage hours, bilevel adherence, pressure support, IPAP/EPAP context, mask leak, residual AHI, residual events, patient symptoms, and follow-up actions.
Usage Hours
Usage hours show whether the patient is using therapy consistently enough to support adherence and compliance review. Even when bilevel therapy is clinically appropriate, poor usage can limit benefit and create documentation challenges.
ResMed patient education explains that myAir can show patients how long they used their CPAP machine, whether the mask leaked, and how many apneas or hypopneas occurred. While the clinical workflow for bilevel patients may be more complex than standard CPAP, usage hours remain one of the first data points staff should review.
In the EHR, usage documentation should include:
- Report date range
- Average nightly usage
- Number of nights used
- Compliance status, when applicable
- Patient-reported barriers
- Outreach completed
- Next follow-up step
If usage is low, the EHR should help staff quickly assign outreach rather than waiting for the next appointment.
Bilevel Adherence
Bilevel adherence should be reviewed in context. A patient may technically use the device but still struggle with pressure comfort, mask leak, dry mouth, awakenings, or persistent symptoms.
The EHR should help the care team document:
Whether the patient is using therapy regularly
Whether usage is improving or declining
Whether the patient reports comfort barriers
Whether adherence problems are related to pressure, leak, mask fit, or education
Whether DME support or provider review is needed
This creates a more meaningful follow-up record than a simple “using” or “not using” status.
Pressure Support and Pressure Settings
Pressure support is especially important for bilevel therapy. In general bilevel PAP, IPAP and EPAP are adjusted to maintain airway patency, and the difference between IPAP and EPAP provides pressure support.
For AirCurve 11 workflows, the EHR should help document pressure-related information from the reviewed report or clinical record, such as:
- IPAP and EPAP setting context
- Pressure support notes
- Patient comfort concerns
- Pressure intolerance symptoms
- Provider review status
- Whether settings were reviewed or need follow-up
Staff should document what was reviewed and what the patient reported, but therapy setting decisions should remain under appropriate provider direction.
Mask Leak
Mask leak is a common issue in PAP therapy and may be especially important for bilevel patients because higher pressures or mouth breathing can make leak more noticeable. ResMed notes that common causes of mask leak include poor mask fit, inadequate cleaning, and mouth leak, and it specifically notes that mouth leak is common if a patient uses a bilevel PAP machine or tends to breathe through the mouth while using a nasal mask or nasal pillows.
A Sleep Medicine EHR should turn mask leak into an action pathway.
For example:
Mild leak: send patient portal education about mask adjustment
Repeated leak: assign RPSGT or sleep technologist follow-up
Severe leak: coordinate DME mask refit
Leak with low usage: contact patient earlier
Leak with residual AHI concern: route to provider review
This keeps the practice proactive and reduces the chance that a correctable mask issue becomes therapy abandonment.
Residual AHI and Residual Events
Residual AHI helps the care team understand whether apnea and hypopnea events are still being detected during therapy. ResMed patient education explains that patients can see how many apneas or hypopneas they had and recommends contacting a doctor or equipment provider when they cannot identify why AHI is changing.
For bilevel patients, residual AHI should be interpreted carefully and in context. Usage, leak, pressure support, patient symptoms, central event concerns where available, and provider judgment all matter.
In the EHR, residual event documentation should include:
- Residual AHI from the reviewed report
- Trend compared with prior reports
- Leak context
- Usage context
- Symptoms such as sleepiness, snoring, awakenings, or poor sleep quality
- Provider review status
- Follow-up plan
The EHR should support physician interpretation, not replace it.
Who Should Review AirCurve 11 Data?
A strong bilevel workflow defines ownership. Without clear role routing, reports may be reviewed inconsistently, provider inboxes can become overloaded, and patient outreach may be delayed.
Sleep Physician or APP
The provider should review clinically significant bilevel issues. This includes persistent residual AHI, pressure support concerns, pressure intolerance, continued symptoms, complex OSA follow-up, possible central event concerns, or any case where therapy changes may be considered.
RPSGT or Sleep Technologist
RPSGTs and sleep technologists can review adherence patterns, mask leak, patient comfort issues, and technical barriers. They are often well positioned to provide patient education and decide whether the issue needs provider escalation.
DME/HME Coordinator
DME/HME staff may support mask refitting, supply replacement, device education, compliance report coordination, and equipment-related questions. Their work should be visible in the EHR so the clinical team can see what has already been done.
Medical Assistant or Care Coordinator
Medical assistants and care coordinators can manage portal reminders, phone outreach, missing reports, questionnaire completion, appointment scheduling, and follow-up task closure.
Billing and Revenue Cycle Team
Billing staff should not interpret bilevel therapy data, but they need clear documentation. Properly organized reports, compliance notes, and follow-up records can reduce avoidable back-and-forth when documentation is needed for payer, DME, or billing workflows.
Recommended EHR Workflow for AirCurve 11 Follow-Up
A practical AirCurve 11 workflow should be repeatable, role-based, and easy for staff to follow.
Step 1: Flag Bilevel Patients Separately
The EHR should identify AirCurve 11 or bilevel PAP patients separately from standard CPAP patients. These patients may require more detailed review of pressure support, IPAP/EPAP context, leak, residual events, and provider oversight.
Useful EHR flags may include:
- Bilevel PAP setup completed
- First adherence check due
- Pressure support review needed
- Leak follow-up needed
- Residual AHI provider review
- Compliance report needed
- DME mask support required
- Follow-up appointment due
This helps the team avoid treating bilevel follow-up as a generic CPAP task.
Step 2: Review AirCurve 11 Data Through the ResMed Workflow
The care team should review available AirCurve 11 data through AirView or the approved ResMed-supported workflow. AirView is designed to help providers access patient data, view reports, manage patient records, and support troubleshooting workflows.
The EHR should not claim that live AirCurve 11 data automatically flows into the chart unless that specific capability is confirmed. Instead, the EHR should make documentation and task routing easy after the report is reviewed.
Step 3: Document Key Findings in the Sleep Medicine EHR
A useful bilevel follow-up note should capture:
- Report source reviewed
- Report date range
- Usage hours
- Bilevel adherence status
- Leak pattern
- Residual AHI or residual event trend
- Pressure support or IPAP/EPAP context
- Patient symptoms or comfort concerns
- Staff action taken
- Provider interpretation, if needed
- Next follow-up step
This creates a clear record for clinical care, patient communication, DME coordination, and revenue cycle support.
Step 4: Route Tasks Based on the Problem
The EHR should route issues based on what the data and patient report show.
Examples:
- Low usage → care coordinator outreach
- Mask leak → RPSGT or DME mask support
- Pressure intolerance → provider review or clinical escalation
- Residual AHI concern → provider review
- Missing report → administrative follow-up
- Supply issue → DME coordinator task
- Patient confusion → portal education plus follow-up call
This prevents every bilevel issue from becoming a disconnected phone call or an untracked note.
Step 5: Connect Follow-Up to the Patient Portal
Patient portal workflows can support bilevel therapy by delivering education, reminders, and structured follow-up questions.
Examples of portal messages include:
“Your bilevel therapy report suggests lower usage than expected. Are you having comfort or mask issues?”
“Your report suggests possible mask leak. Please check your mask fit or contact our team.”
“Please complete your bilevel PAP follow-up questionnaire before your appointment.”
“Your provider reviewed your therapy report and recommends a follow-up discussion.”
The EHR should save portal communication so the care team can see the full outreach history.
Step 6: Close the Loop
Every task should end with documentation. Staff should record whether the patient was reached, what was discussed, what action was taken, and whether provider review remains open.
Example documentation:
“AirCurve 11 bilevel report reviewed through ResMed workflow. Usage hours, leak, residual AHI, and pressure support context documented. Patient reports mask discomfort and difficulty tolerating pressure. RPSGT task created for mask troubleshooting. Provider review requested for pressure-related concerns. Portal education sent.”
When Should Staff Contact the Patient?
Staff should contact the patient when AirCurve 11 data suggests a risk to bilevel adherence, therapy effectiveness, patient comfort, compliance documentation, or follow-up completion.
Common outreach triggers include:
- Low usage hours
- Declining PAP adherence
- Persistent or high mask leak
- Residual AHI trend requiring review
- Pressure support or pressure intolerance concerns
- Patient reports discomfort, dry mouth, anxiety, or mask problems
- Missing therapy report when follow-up is due
- Compliance window approaching
- DME supply or mask replacement issue
- Missed sleep apnea follow-up appointment
For bilevel patients, early outreach is especially valuable because small comfort problems can quickly become nonadherence.
Revenue Cycle Value of Better Bilevel Documentation
AirCurve 11 follow-up is clinical, but it also affects operations and revenue cycle performance.
When bilevel therapy documentation is incomplete, practices may face:
- Missing compliance reports
- Delayed follow-up visits
- DME coordination gaps
- More staff back-and-forth
- Payer documentation problems
- Harder chart review before appointments
- Unclear patient outreach history
- Provider time spent searching for report details
A better Sleep Medicine EHR workflow can help organize:
- Bilevel adherence documentation
- Usage hours and compliance notes
- Pressure support context
- Mask leak follow-up
- Residual AHI review
- Attached or referenced reports
- Patient portal communication
- Provider review status
- Billing-supporting documentation
This is why AirCurve 11 integration should be evaluated as a complete workflow strategy, not just a technical connection.
Buyer-Focused Checklist for Sleep Medicine EHR Selection
When evaluating a Sleep Medicine EHR for AirCurve 11 workflows, practices should ask practical questions.
Does the EHR Support Bilevel-Specific Documentation?
The EHR should support fields or templates for usage hours, bilevel adherence, pressure support, leak, residual AHI, patient symptoms, and follow-up action.
Can Staff Attach or Reference AirView Reports?
Reports should be easy to upload, attach, reference, or summarize so providers, staff, and billing teams can find them quickly.
Can Tasks Be Routed by Role?
A strong EHR should route tasks to providers, RPSGTs, sleep technologists, care coordinators, DME/HME coordinators, and billing staff.
Does the Patient Portal Support PAP Follow-Up?
The patient portal should support reminders, education, questionnaires, and documented patient communication.
Does the Vendor Explain Integration Honestly?
Avoid vague claims. A trustworthy vendor should explain what is supported directly, what requires configuration, and what depends on ResMed, AirView, third-party systems, or implementation scope.
Can the Workflow Support Compliance and Revenue Cycle Needs?
The EHR should support clean documentation for compliance review, DME coordination, payer documentation, and billing support.
How 1st Providers Choice Supports Bilevel Sleep Therapy Workflows
1st Providers Choice supports specialty-specific Sleep Medicine EHR workflows for practices managing CPAP, APAP, bilevel PAP, and complex sleep apnea follow-up.
For AirCurve 11 patients, the priority is to make bilevel therapy follow-up more organized. That means helping teams document report review, track usage hours, monitor mask leak and residual AHI, capture pressure support context, assign follow-up tasks, support patient portal communication, and keep compliance documentation easier to find.
A well-designed Sleep Medicine EHR should help the practice move from scattered follow-up to a clear process:
- Review AirCurve 11 data through the appropriate ResMed workflow.
- Document findings in the patient chart.
- Route issues to the right staff member.
- Contact the patient when needed.
- Support provider interpretation.
- Maintain compliance-ready documentation.
- Reduce operational friction for staff.
FAQs
1. What data matters most for AirCurve 11 integration?
The most important data includes usage hours, bilevel adherence, pressure support, IPAP/EPAP context, mask leak, residual AHI, report date range, patient symptoms, and follow-up actions. These data points help the sleep team understand whether the patient is using therapy, whether comfort issues are affecting adherence, and whether provider review is needed.
2. Does AirCurve 11 integrate directly with every Sleep Medicine EHR?
No. Practices should not assume that AirCurve 11 connects directly to every EHR or sends real-time data into every system. Unless vendor documentation confirms a specific interface, it is safer to describe the workflow as AirView review plus EHR documentation, report attachment, task routing, patient portal communication, and follow-up tracking.
3. Who should review AirCurve 11 bilevel compliance data?
RPSGTs, sleep technologists, care coordinators, DME/HME staff, and providers may all participate. Providers should review clinically significant concerns, such as pressure intolerance, persistent residual AHI, complex OSA follow-up, ongoing symptoms, or cases where therapy changes may be considered.
4. When should staff contact a bilevel therapy patient?
Staff should contact the patient when usage hours are low, PAP adherence is declining, mask leak is persistent, residual AHI needs review, pressure support concerns are reported, data is missing, or the compliance review window is approaching. Early outreach can help address comfort barriers before the patient stops therapy.
5. How should AirCurve 11 reports be documented in the EHR?
The EHR note should include the report date range, usage hours, bilevel adherence status, pressure support context, leak pattern, residual AHI, patient concerns, outreach completed, task routing, and provider interpretation when appropriate. The practice should attach, reference, or summarize the report according to its documentation policy.
Conclusion
AirCurve 11 bilevel therapy follow-up requires more than basic CPAP compliance tracking. These patients may need careful review of usage hours, pressure support, mask leak, residual AHI, comfort concerns, and provider-directed follow-up.
A practical AirCurve 11 integration strategy should help sleep teams review AirView-supported data, document bilevel adherence, route follow-up tasks, communicate through the patient portal, and maintain compliance-ready records without overclaiming direct device-to-EHR connectivity.
For sleep medicine practices, the right EHR should make complex bilevel follow-up easier to manage, easier to document, and easier to connect with patient adherence and revenue cycle workflows.
1st Providers Choice can help sleep practices build a more organized Sleep Medicine EHR workflow for AirCurve 11 follow-up, bilevel PAP documentation, patient communication, compliance review, and revenue-cycle support.